
-
 Kphb Branch
+91 9111674111
-
Tarnaka Branch
+91 9100001201
- Book Appointment
+91 9111674111
+91 9100001201
Vascular Surgery
A diabetic foot ulcer is an open wound that can become infected and may be difficult to heal, particularly when diabetes-related nerve damage or reduced blood flow is present. Early assessment helps identify infection, pressure, circulation problems and other factors affecting healing.
Consultation: KPHB vascular specialist; Tarnaka vascular consultation by prior appointment
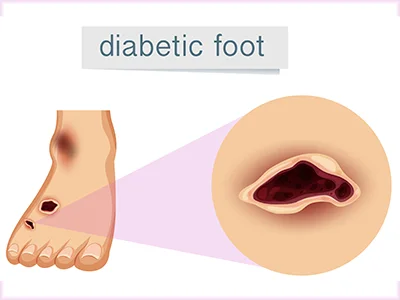
Treatment may involve wound care, infection management, pressure relief and evaluation of blood flow. Some ulcers require specialist procedures or surgery.
A diabetic foot ulcer is an open sore or wound on the foot that occurs in a person with diabetes. Nerve damage can reduce pain sensation, while poor circulation can impair healing. Infection, pressure, repeated injury and uncontrolled blood glucose can make a wound harder to heal. Prompt medical assessment is important because severe infection or tissue damage can threaten the foot.
Diabetic foot ulcers commonly develop when diabetes affects sensation, circulation or the ability of the foot to withstand repeated pressure. A small blister, cut, callus or pressure area may go unnoticed when protective sensation is reduced.
A wound can become infected and, in more advanced cases, infection may involve deeper tissues or bone. Reduced blood flow can further delay healing. For this reason, treatment should address not only the wound but also the factors that caused or are preventing healing.
People with diabetes may have reduced sensation and may not notice a wound until it has become larger or infected.
Reduced sensation can make cuts, burns, blisters and pressure injuries difficult to notice.
Poor circulation can reduce oxygen and nutrient delivery needed for tissue repair.
Poorly controlled diabetes can contribute to nerve, vascular and immune problems that affect healing.
Increased mechanical pressure on the feet may contribute to skin breakdown and delayed healing.
The risk of nerve and vascular complications can increase with the duration of diabetes.
High blood pressure, high cholesterol, smoking and other vascular risk factors can affect foot health.
A diabetic foot problem can involve an ulcer, neuropathy, infection or circulation changes. Symptoms vary, and reduced sensation can make a serious wound surprisingly painless.
A cut, blister or wound that does not heal normally.
Drainage from a wound may indicate infection and needs assessment.
Increasing redness, warmth or swelling can occur with inflammation or infection.
Neuropathy may cause numbness, burning, tingling or reduced pain sensation.
Discoloration, dark tissue or changes around a wound can be warning signs.
Calluses, repeated pressure and deformities may contribute to ulcer formation.
Evaluation looks beyond the visible wound. A clinician may assess the ulcer's size and depth, surrounding skin, infection, sensation, foot pressure, pulses and blood flow. Additional tests are selected according to the clinical findings.
The wound is assessed for size, depth, drainage, tissue condition and surrounding inflammation.
Sensation may be assessed to identify diabetic neuropathy and reduced protective sensation.
When poor blood flow is suspected, vascular examination and appropriate vascular testing may be needed.
Blood tests may be used when infection, inflammation or other systemic concerns need evaluation.
X-ray and, when indicated, MRI or other imaging can help evaluate deeper tissue or bone involvement.
The appropriate investigations depend on the wound, symptoms and clinical examination. Not every patient requires every test.
Diabetic foot ulcer treatment depends on wound severity, infection, tissue involvement, pressure on the foot, blood flow, neuropathy and overall health. Treatment often requires more than one approach.
Appropriate wound cleaning, dressings and regular assessment help create conditions that support healing.
A trained clinician may remove non-viable tissue after assessing the wound and circulation. Do not cut away callus, black tissue or an ulcer at home.
Ask about an offloading device selected for the wound, infection and circulation. A regular shoe or dressing alone may not adequately reduce pressure; do not make your own cast.
Suspected infection needs prompt clinician-directed antibiotics. An uninfected ulcer does not need antibiotics simply to help it heal; do not use leftover tablets or creams.
If poor circulation is contributing to non-healing, vascular evaluation may identify whether revascularization such as angioplasty or bypass is appropriate.
Selected patients may require procedures such as debridement, reconstruction, skin grafting or, when tissue cannot be preserved, amputation.
A diabetic foot ulcer may persist if infection, pressure, neuropathy or poor circulation is not addressed. A specialist assessment can help determine the priorities for care.
Removal of dead or infected tissue may be required when wound care alone is not sufficient.
Angioplasty, bypass or another vascular procedure may be considered when inadequate blood flow is preventing healing.
In selected wounds, a skin graft may be considered after the wound bed is suitable for closure.
Selected deformities or structural problems may require reconstructive treatment to improve function or reduce repeated pressure.
Deeper infection may require surgical removal of infected tissue or other specialist treatment.
Amputation is generally considered only when severe infection, tissue death or non-salvageable damage makes preservation of the affected part unsafe or impossible.
Surgery is not automatically required for every diabetic foot ulcer. The goal is to control infection, preserve viable tissue, support healing and protect function whenever possible.
Healing may take weeks or months and cannot be predicted from a photograph or a dressing alone. Ask the treating team how wound measurements and circulation will be reassessed if progress is slow.
Healing can be affected by ulcer size and depth, infection, blood flow, neuropathy, pressure, blood glucose control, nutrition and adherence to the treatment plan.
A wound that is improving should be monitored regularly. If an ulcer becomes larger, develops new drainage, changes color or develops increasing redness or swelling, contact a healthcare professional.
KPHB: Dr. Puneeth Joopalli, Vascular & Endovascular Surgeon, MBBS, MS, DNB (NIMS), 15+ years experience, takes on-call appointments at KPHB. Call +91 9111674111 to confirm the slot.
Tarnaka: For a vascular consultation at Tarnaka, call ahead to confirm the attending clinician. Call +91 9100001201 to confirm the clinician and appointment time.
KPHB address: H.No 15-24-212, MIG-212, Road Number 1, KPHB Phase 1, Kukatpally Housing Board Colony, Hyderabad, Telangana 500072.
Tarnaka address: H.No 12-5-30, White House, Moula Ali Road, South Lalaguda, Tarnaka, Secunderabad, Telangana 500017.
Bring your medication list, allergies, glucose records, previous culture reports, scans and details of earlier dressings or antibiotics. Confirm which wound-care, vascular or surgical services can be arranged at the selected branch and whether referral is needed.
 Vascular & Endovascular Surgeon
MBBS, MS, DNB (NIMS)
15+ Years Experience | KPHB; Tarnaka on call
12:00 PM – 5:00 PM | Confirm appointment
View Vascular SurgeryEarly warning signs can include a persistent open wound, redness, swelling, warmth, drainage, skin changes or a blister that is not healing normally. Reduced sensation may make the wound painless.
Regular foot inspection, good foot hygiene, appropriate footwear, diabetes management and regular foot checks can help reduce the risk. Prompt attention to minor injuries is also important.
Treatment depends on the wound and its underlying causes. Care may include wound dressings, debridement, pressure relief, infection treatment, vascular evaluation and selected surgical procedures.
Contact a clinician today for any new ulcer, even without pain. Fever, black tissue, a cold or pale foot, rapidly spreading infection or severe illness requires emergency assessment; do not wait for a routine appointment.
Severe infection, extensive tissue damage or non-salvageable tissue can sometimes lead to amputation. Early treatment aims to control infection, support healing and preserve viable tissue whenever possible.
Healing time varies according to wound size and depth, infection, circulation, neuropathy, pressure, diabetes control and treatment. The timeline is individual and cannot be guaranteed.
No. Many ulcers are managed with wound care, pressure relief and treatment of infection or other underlying problems. Surgery is considered when clinically necessary.
Yes. Reduced blood flow can impair tissue oxygenation and healing. When an ulcer is not healing as expected, vascular assessment may be appropriate.
If you have a diabetic foot wound that is not healing, shows signs of infection or is associated with numbness or circulation problems, a specialist assessment can help identify the next step.
Find Our Kukatpally and Tarnaka Branches
H.No 15-24-212, MIG-212, Rd Number 1, K P H B Phase 1, Kukatpally, Hyderabad, Telangana 500072
H.No:-12-5-30, WhiteHouse, Moula Ali Rd, South Lalaguda, Tarnaka, Secunderabad, Telangana 500017