
-
 Kphb Branch
+91 9111674111
-
Tarnaka Branch
+91 9100001201
- Book Appointment
+91 9111674111
+91 9100001201
At My Health Hospitals, book a urology consultation with Dr. Davalla Sandeep at Kukatpally (KPHB) or Dr. Jayanth Reddy at Tarnaka. Bring your scan images, reports and current medicine list. Ask which tests or procedures are needed, where they will take place and what preparation is required; a consultation listing does not confirm round-the-clock testing or surgical availability at both branches.
Kidney stones are hard deposits formed from substances in urine. They may remain in a kidney or move into a ureter, the tube that carries urine from the kidney to the bladder.
Concentrated urine can encourage stone formation. Fluid losses in hot weather may increase the amount you need to drink, but prevention also depends on stone composition, diet, medical history and any prescribed fluid restriction.
Some stones cause no symptoms and are found on imaging. Others cause pain or interfere with urine drainage. Symptoms alone do not show the stone’s size, exact location or whether the kidney is draining normally.

Follow-up matters: Relief of pain does not prove that a stone has passed or that blockage has resolved. Follow the clinician’s plan for reassessment and seek urgent help for fever, reduced urine or worsening symptoms.
A 4 mm stone in a ureter is different from a 4 mm stone still inside the kidney. The chart below explains what to discuss; it is not a prediction of passage or a medicine prescription. A follow-up plan is needed if observation is chosen.
| Reported Stone Size | Can It Pass? | Follow-up Planning | What to Discuss With the Urologist | When Active Treatment May Be Needed |
|---|---|---|---|---|
| 1–3 mm | A small ureteric stone may pass; a kidney stone may remain in place. | Agree a review plan; do not assume symptom relief proves passage. | Pain relief, imaging findings and whether observation is suitable. | Infection, blockage, uncontrolled symptoms or impaired kidney function. |
| 4 mm | May pass, particularly when low in the ureter; not guaranteed. | Ask when and how passage or drainage should be checked. | Stone location and supervised observation; medicines are not required for every small stone. | Complications or failure of an agreed observation plan. |
| 5 mm | Passage is possible, but size alone cannot predict the outcome. | Regular review based on symptoms and imaging. | Whether observation or a procedure offers the better balance for your case. | Persistent pain, obstruction, infection or reduced kidney function. |
| 6 mm | Some ureteric stones pass; others need removal. | A clinician should define the review and escalation plan. | Location, blockage and whether selected medical expulsive therapy is appropriate. | Complications, low likelihood of passage or unsuccessful observation. |
| 7–10 mm | Passage becomes less likely as size increases. | Avoid unmonitored waiting. | Observation in selected cases versus ureteroscopy or shockwave treatment. | Persistent symptoms or obstruction, or a decision to remove the stone. |
| Over 10–20 mm | Spontaneous passage is generally unlikely; kidney stones require an individual plan. | Monitor or treat according to symptoms, growth and clinical risk. | Stone burden and location; suitability of RIRS, shockwave treatment or PCNL. | Symptoms, growth, infection, obstruction or other reasons for removal. |
| Over 20 mm / staghorn | Usually needs specialist treatment planning. | Assess infection, kidney function and procedural fitness. | PCNL is commonly considered for larger renal stones; more than one treatment may be needed. | Plan timing and method after assessment; urgent drainage may precede stone removal if infection is present. |
Size is only part of the decision: Location, infection, pain, blockage, kidney function and your circumstances affect whether waiting is appropriate. Do not wait for a set number of weeks if symptoms worsen. Medicines to assist passage are prescribed only for selected patients.
Kidney stone pain can affect the back, side, lower abdomen or groin and may come in waves. These symptoms overlap with other conditions. Examination and appropriate tests are needed to confirm a stone and assess drainage.
| Symptom or Finding | What You May Notice | Why Assessment Matters |
|---|---|---|
| No symptoms | A stone may be found on a scan performed for another reason. | Ask whether monitoring is appropriate and what follow-up is needed. |
| Back or side pain | Pain may come in waves and spread to the abdomen or groin; nausea or vomiting can occur. | The pain pattern alone cannot confirm a stone or pinpoint its location. |
| Urinary symptoms | Blood in urine, burning, urgency or difficulty passing urine may occur. | Other urinary problems can cause these symptoms. Fever or inability to urinate needs urgent attention. |
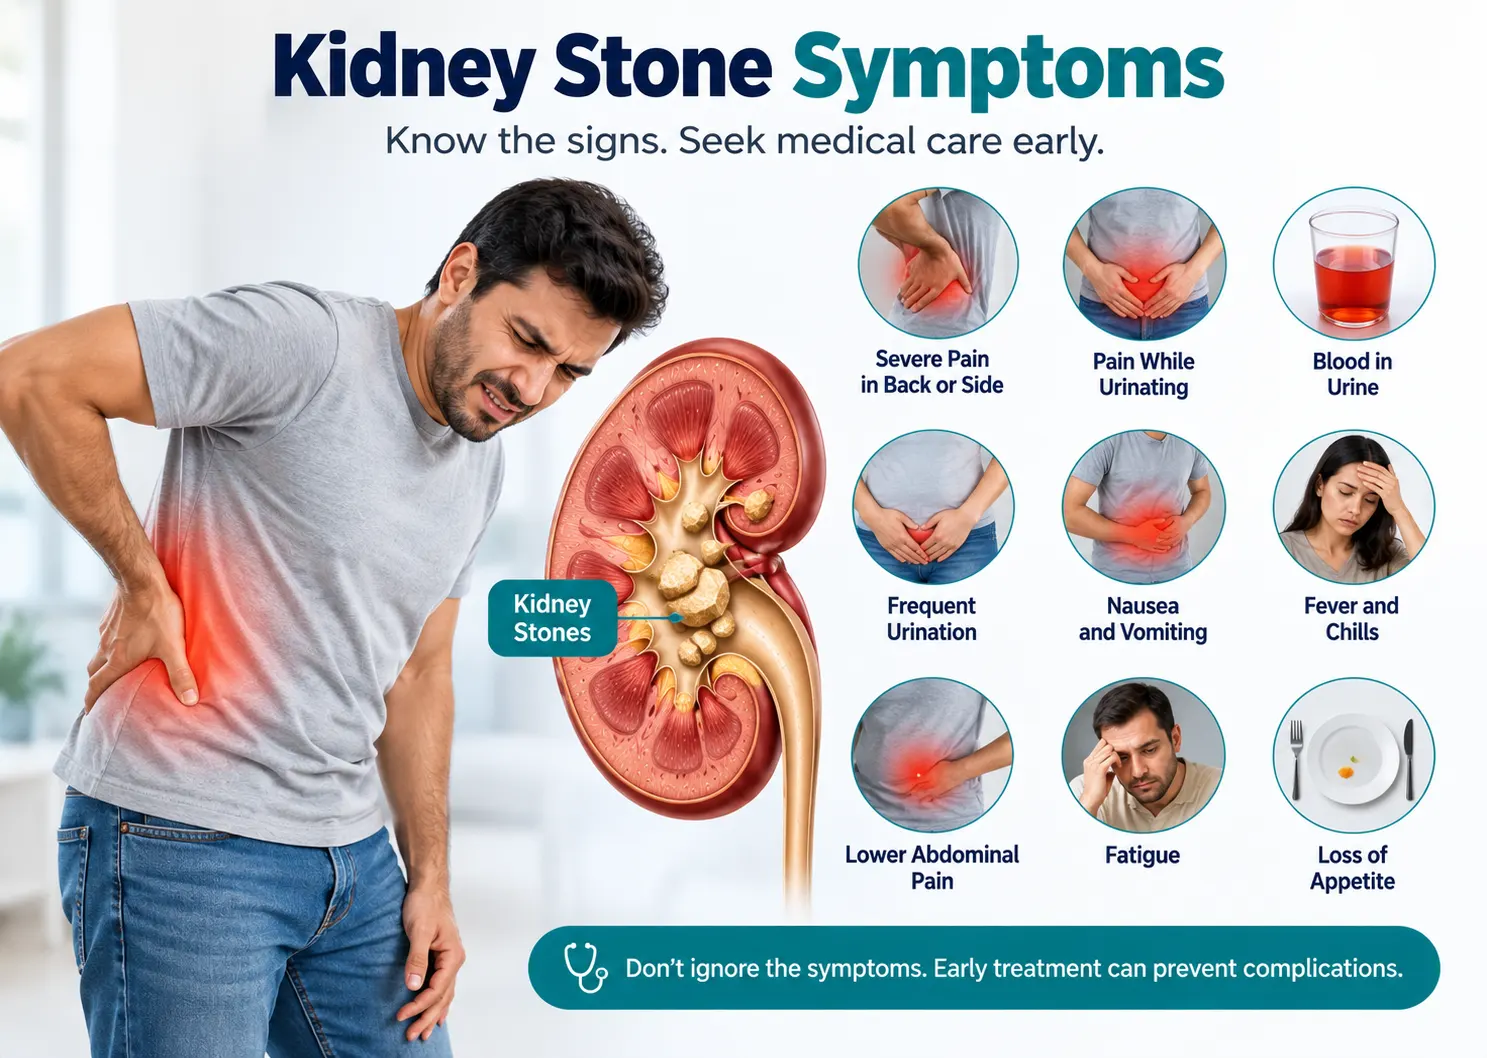
Seek urgent medical assessment rather than waiting for a routine appointment if stone symptoms are accompanied by any of the following:
The clinician combines your symptoms and medical history with appropriate urine, blood and imaging tests. Not every patient needs every test. Ask the branch about the specific investigation advised and where it can be arranged.
Ultrasound does not use ionising radiation and can help assess stones and kidney swelling. It may not show every ureteric stone. Imaging choice needs particular care in pregnancy and children.
A non-contrast CT can provide detailed information about a stone’s size, location and density when clinically appropriate. Radiation exposure and alternatives should be considered; CT density alone does not establish stone composition or the complete treatment plan.
Urine testing can look for blood and signs of infection; a culture may be needed. Suspected infection with obstruction needs urgent assessment, and infection treatment may affect the timing of a planned procedure.
Blood tests can assess kidney function and other relevant factors. Stone analysis and selected urine testing may help investigate recurrence and tailor prevention. Ask how results will influence your care.
Observation, shockwave treatment and endoscopic or percutaneous surgery have different benefits and risks. The surgeon considers stone burden, anatomy, infection, bleeding risk and your preferences. Confirm the proposed procedure and treating facility before admission.
ESWL uses shockwaves from outside the body to break a suitable stone into fragments. Fragments must then pass in urine, and repeat sessions or another procedure may be needed.
Ureteroscopy uses a scope passed through the urinary passage to reach a ureteric stone. The surgeon can remove or fragment it, sometimes using a laser. A temporary stent may be needed.
RIRS uses a flexible scope passed through the urinary passage to treat stones inside the kidney. Laser fragmentation may be used; staged treatment or a temporary stent may be necessary.
PCNL accesses the kidney through a small tract in the back. It is often considered for larger or complex kidney stones. The tract size, tubes and need for further treatment depend on the case.
| What to Compare | ESWL | URSL / Ureteroscopy | RIRS | Mini-PCNL / PCNL |
|---|---|---|---|---|
| Usual role | Selected kidney or ureteric stones suitable for shockwaves. | Stones in the ureter requiring endoscopic treatment. | Selected stones within the kidney. | Larger or complex kidney stone burdens. |
| Selection factors | Size, location, density, anatomy and ability to pass fragments. | Location, impaction, access, infection and patient factors. | Stone burden, location, anatomy and access. | Stone burden, anatomy, infection and procedural fitness. |
| Access route | Shockwaves applied from outside the body. | Scope through the natural urinary passage. | Flexible scope through the natural urinary passage. | Tract through the skin into the kidney. |
| Anaesthesia | Pain relief or anaesthesia as advised. | Anaesthesia planned for the patient and procedure. | Anaesthesia discussed during pre-operative assessment. | Anaesthesia discussed during pre-operative assessment. |
| Further treatment | Repeat sessions or another procedure may be needed. | Residual stones or difficult access may require further treatment. | A staged procedure may be needed for some stone burdens. | Additional treatment may be needed for complex or residual stones. |
| Stay & recovery | Often an outpatient procedure; follow the discharge advice. | Day care or admission depending on recovery and clinical needs. | Stay and return to activity depend on recovery and the treatment plan. | Admission and recovery depend on stone complexity and clinical progress. |
| Stent or drainage tube | Used in selected circumstances. | A temporary ureteric stent may be placed. | Pre- or post-procedure stenting may be advised. | A ureteric stent or nephrostomy tube may be used. |
Request a current written estimate after assessment and confirmation of the procedure and treating branch. Use the checklist below to compare inclusions, exclusions and possible additional charges. No hospital-approved price range is published here.
| Procedure | Estimate to Request | Ask Whether the Quote Includes | Factors That Can Change the Bill |
|---|---|---|---|
| ESWL | Quote for the planned sessions | Number of sessions, imaging, pain relief, medicines and follow-up. | Repeat sessions, additional treatment and any stent or admission needed. |
| Laser URSL | Quote for the proposed ureteroscopy | Surgeon and anaesthesia fees, theatre charges, consumables, stent and planned stay. | One or both sides, complexity, room category, additional stay and stent removal. |
| RIRS | Quote for planned RIRS and any stages | Scope-related consumables, laser, anaesthesia, theatre, stent and planned stay. | Stone burden, consumables, pre-stenting, staged procedures and follow-up treatment. |
| Mini-PCNL / PCNL | Quote for the proposed PCNL plan | Procedure, anaesthesia, consumables, planned stay, tubes and follow-up. | Complexity, additional treatment, drainage needs, monitoring and length of stay. |
Cashless eligibility depends on the insurer’s current hospital network, your policy, proposed treatment and pre-authorization. Ask the branch and insurer about documents, co-payments, room limits, deposits and non-payable items before planned admission.
For self-pay treatment, request an itemised written estimate. Clarify what is included and how repeat procedures, extra stay, additional tests, medicines, stent removal or complications would change the final bill. Ask the billing team about current payment options.
This page provides general information about kidney stones. For doctor profiles, current consultation timings, branch contact details and address information, use the relevant branch page.
View the Kukatpally-specific urology consultation information, including the listed doctor details, appointment contact and branch address.
View the Tarnaka-specific urology consultation information, including the listed doctor details, appointment contact and branch address.
Stone treatment does not prevent all future stones. Follow-up can check recovery, residual stones and prevention needs. Stone analysis and, for selected patients, metabolic testing can guide a more individual prevention plan.
A temporary double-J (DJ) stent may be placed between the kidney and bladder to support drainage. Not every patient needs one. Ask why it is being placed and obtain the planned removal or exchange date in writing.
Prevention should match the stone type, medical conditions and any fluid restriction. A clinician or dietitian can advise on fluids, salt, dietary calcium, oxalate and animal protein without unnecessary food restrictions.
Further reading: See our kidney stone diet guide. Public patient information is also available from NIDDK and the EAU urolithiasis guideline.
Answers about observation, procedures, costs and follow-up. Use these answers to prepare questions for your consultation.
Some small stones in the ureter pass with supervised observation, but a stone still in the kidney may remain there. Size alone cannot predict passage. Location, infection, blockage, pain and kidney function determine whether observation, prescribed medicine or a procedure is appropriate. Agree a follow-up plan and seek urgent help if symptoms worsen.
URSL uses a scope through the urinary passage to treat a ureteric stone. RIRS uses a flexible scope through the urinary passage to reach stones within the kidney. PCNL reaches the kidney through a tract in the back and is often considered for larger or complex stones. All require individual assessment, and further treatment may be needed.
A current estimate requires assessment, a proposed procedure and confirmation of the treating branch. Request an itemised written quote showing professional fees, anaesthesia, investigations, consumables, planned stay, stent placement and removal, follow-up and any repeat or staged treatment. Ask about exclusions, additional charges and insurer authorisation.
Use the dedicated Kukatpally or Tarnaka kidney stone consultation page for the branch-specific doctor profile, contact number, address and listed consultation window. Confirm the current appointment date and slot with the branch before travelling.
Pain can affect the back, side, lower abdomen or groin, sometimes in waves. Blood in urine, nausea or urinary symptoms may occur. Pain location alone cannot diagnose a stone or distinguish it reliably from other causes of back or abdominal pain; clinical assessment and appropriate tests are needed.
RIRS is performed with anaesthesia, but postoperative discomfort or stent symptoms can occur. Day care or admission depends on recovery, infection, the procedure and other health needs. Ask for an individual plan for pain relief, discharge and return to work rather than a guaranteed timeline.
A temporary ureteric stent may support drainage before or after a procedure. The reason, duration and removal method depend on the clinical plan. Obtain the removal or exchange date in writing, keep the appointment and seek prompt advice for fever, worsening pain or difficulty passing urine.
Some uric acid stones can be dissolved with clinician-supervised treatment and monitoring. This does not apply to every stone type, and medicines or citrate products should not be started from a web page. Infection, obstruction and kidney function affect the treatment plan.
Consult Dr. Davalla Sandeep at Kukatpally or Dr. Jayanth Reddy at Tarnaka with your existing reports. Ask about observation, treatment choices, costs and follow-up. Routine appointment lines are not a substitute for urgent emergency assessment.
Patient Information: This guide supports discussion with a qualified clinician and does not replace assessment, diagnosis or a personalised treatment plan. Procedure availability and estimates must be confirmed with the relevant branch. General references: NIDDK treatment guidance, NIDDK symptoms information, EAU urolithiasis guideline.
Find Our Kukatpally and Tarnaka Branches
H.No 15-24-212, MIG-212, Rd Number 1, K P H B Phase 1, Kukatpally, Hyderabad, Telangana 500072
H.No:-12-5-30, WhiteHouse, Moula Ali Rd, South Lalaguda, Tarnaka, Secunderabad, Telangana 500017